Cart |  Login

Lymphedema Therapy Source


  • About
    • Founder
    • Awards
  • Services
    • Patients
      • Insurance
      • FAQS
    • Healthcare Professionals
      • Clinics and Hospitals
      • Physicians
        • Manual Lymphatic Drainage (MLD)
        • Indications for Treatment
        • Research
      • Home Health Agencies
  • Learn
    • Before and After Photos
  • News
  • e-Shop

MLD After Joint Replacement: A Key to Post-Surgical Recovery

Arthritis can severely impact mobility. Many individuals with past sports injuries or those who participate in high-impact activities (like tennis) eventually require joint replacements in later years. When joint replacements occur—whether shoulder, knee, finger joints, or elsewhere—there is substantial mechanical and structural trauma to the body during surgery.

Body Response to Trauma

The body does not distinguish a planned surgical procedure from an accidental injury. It responds to surgical trauma with an acute inflammatory cascade, characterized by the accumulation of fluid and swelling. Ironically, what we often view as a negative side effect is actually a required biological process that builds the physical framework for new tissue. Completely preventing this acute response would stall or entirely halt the healing process.

Why Protein-Rich Fluid is Beneficial and Necessary

When tissue is cut during surgery, blood vessels briefly constrict and then dilate, becoming highly permeable or “leaky.” This allows plasma fluid packed with specialized proteins to flood the interstitial space around the wound, serving critical biological functions:

  • Building the Physical Scaffold: This protein-rich fluid contains high concentrations of fibrinogen. Once it leaks into the wounded tissue, it converts into a sticky fibrin mesh. This mesh acts as a literal scaffolding or biological glue that closes the gaps between cut tissues and provides a physical pathway for new cells to crawl across and rebuild.
  • Fueling Cellular Growth: The fluid carries proteins, including albumins and globulins, which maintain local osmotic pressure and provide the essential amino acid building blocks that local cells, such as fibroblasts, need to manufacture new collagen.
  • Transporting Growth Factors: It functions as a specialized chemical highway. Soluble signaling molecules, cytokines, and growth factors travel through this fluid to signal the regional cellular network exactly how much tissue needs to be repaired.
  • Defending the Wound: The swelling creates a localized, high-pressure zone that slows down local circulation just enough to allow white blood cells, such as neutrophils and macrophages, to adhere to the vessel walls and migrate directly into the injury site to destroy invading bacteria.
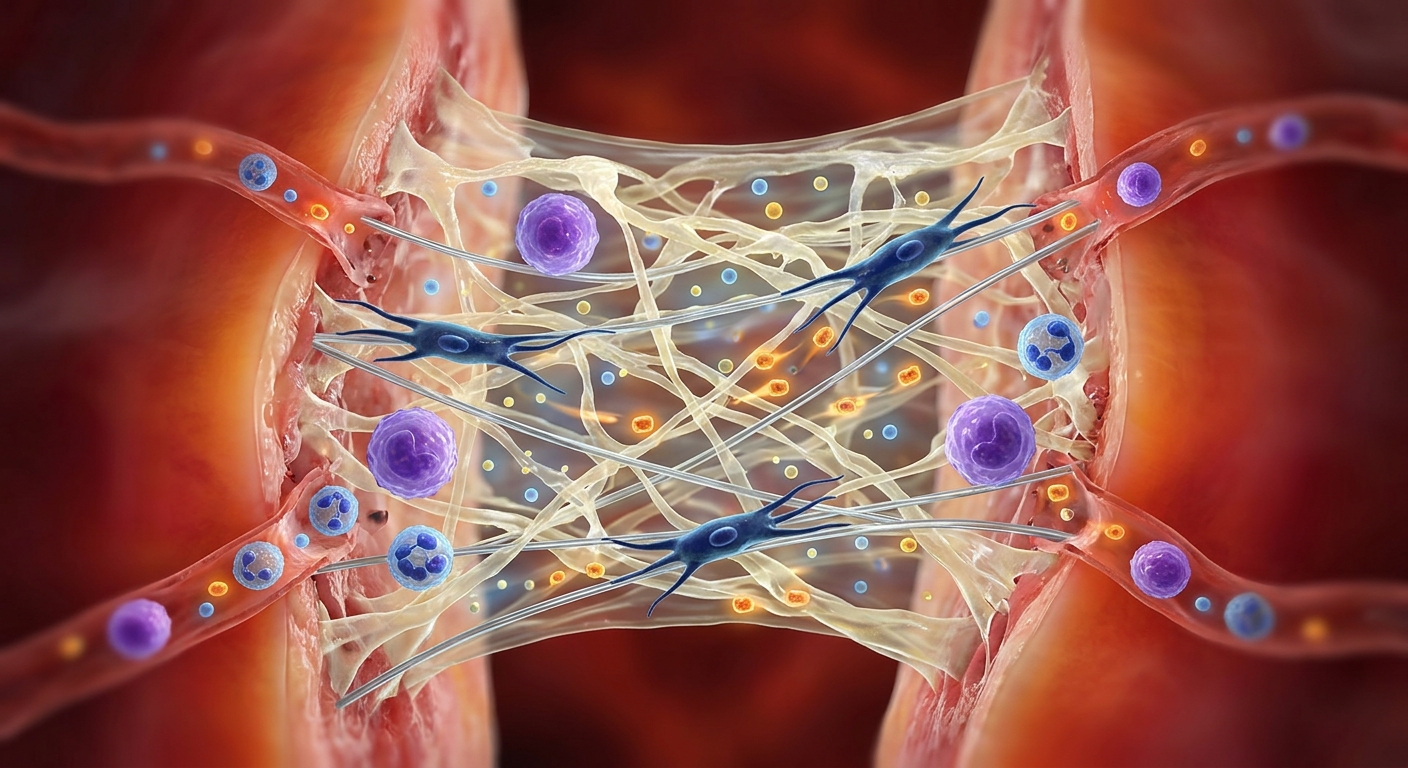
Depiction of swelling and the physical scaffold

Wouldn’t It Be Better to Reduce It?

It is a delicate balance of timing and volume, rather than a question of eliminating the fluid entirely:

  • In the First 24–72 Hours: You do not want to completely eliminate inflammation or swelling. Stopping it aggressively during this phase can result in poor wound healing, weak scar tissue formation, or a failure of tissues to knit back together.
  • After the First 72 Hours: Once the fibrin scaffold is built and the cellular cleanup crew has finished, the protein-rich fluid has served its purpose. If it stagnates and stays in the tissue too long, it thickens, causing chronic stiffness, severe pain, and a buildup of pressure that cuts off the oxygen supply needed for the next stage of healing.

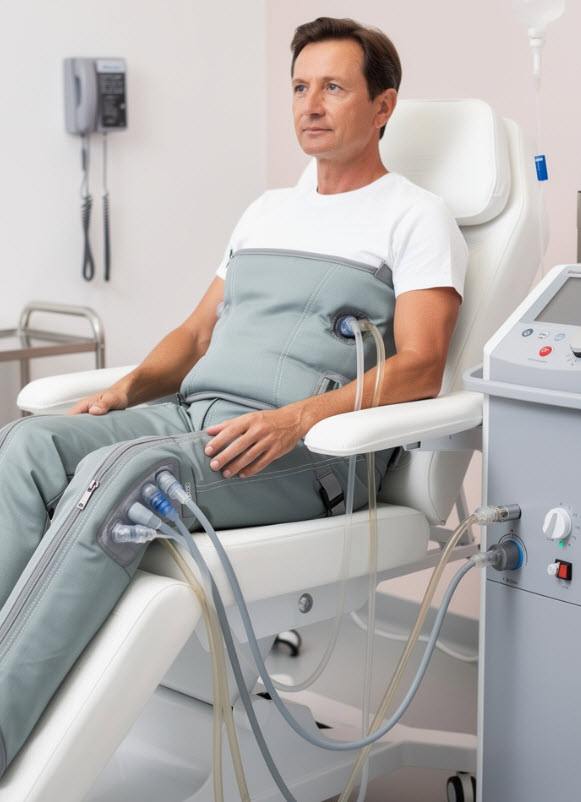
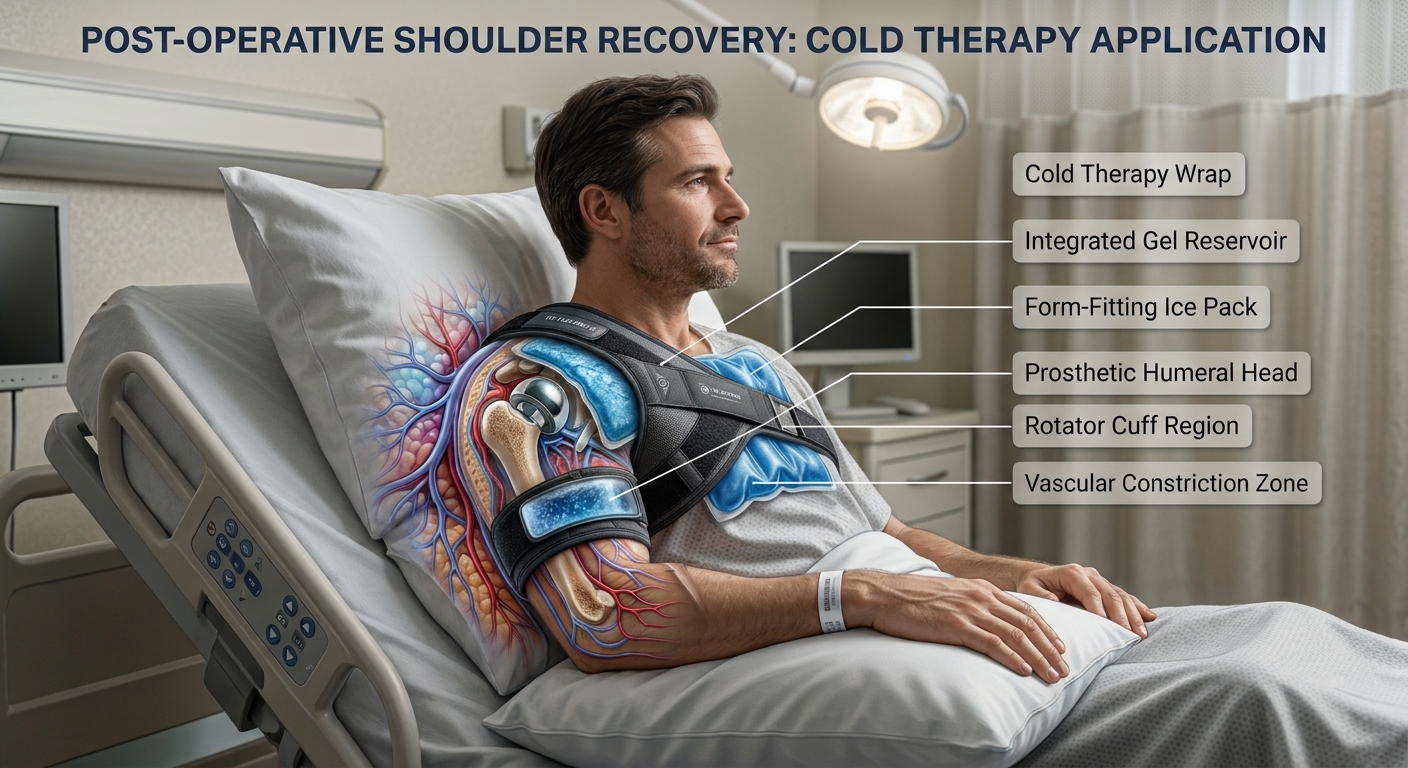
To prevent this stagnation from occurring, post-surgical rehabilitation relies on a strategic sequence of medical interventions—including early vasoconstriction, targeted compression, anti-inflammatories, and specialized drainage techniques. [image]

These treatments are not designed to stop the natural healing process from happening. Instead, they are used to cap the peak of the swelling so that it does not become so overwhelming that it compresses local capillaries and collapses the very circulation required to deliver these healing proteins.

Manual Lymphatic Drainage (MLD) After Surgery

Manual Lymphatic Drainage (MLD) is a specialized physical intervention that becomes highly beneficial once the initial acute inflammatory influx begins to stabilize, generally around or after the 72-hour mark. Depending on the specific surgical procedure and surgeon clearance, it can sometimes begin as early as 24 to 48 hours post-op to manage rapidly accumulating fluid.

The primary reason why early interventions like ice and compression are used immediately, rather than delayed until after 72 hours, comes down to the physiological difference between fluid prevention versus fluid clearance.

1. The Timeline Shift: Prevention vs. Moving Fluid

Ice and compression are used immediately to control the inflow of fluid, while MLD is used later to manage the outflow.

  • 0 to 72 Hours (The Inflow Phase): The body is aggressively opening up blood vessels to dump fluid and proteins into the wound. Cold therapy and early compression work right away to narrow these blood vessels and physically squeeze the tissue space. This acts as a barrier that caps the peak amount of fluid that can pool in the first place. If you waited 72 hours to start compression and ice, the tissue would already be massively engorged, and the initial opportunity to limit fluid accumulation would be lost.
  • After 72 Hours (The Outflow Phase): Once the fluid is already inside the tissue and the blood vessels have stabilized, cold therapy loses its primary benefit. You cannot freeze fluid out of a tissue. This is where MLD comes in. MLD does not stop fluid from entering; it uses gentle, rhythmic movements to stretch the skin, open damaged or sluggish lymphatic channels, and push the trapped fluid out of the area so the body can reabsorb it into central circulation.

2. The Danger of Ice After 72 Hours

Using ice aggressively after the 72-hour window can actually work against recovery. Once the initial swelling peak passes, the body needs robust blood flow to deliver oxygen and fresh nutrients to repair the cellular matrix. Because ice constricts blood vessels, leaving it on long-term slows down local circulation. This can cause the stagnant, protein-rich fluid to thicken and become gelatinous, which leads to tissue hardness (fibrosis) and severe joint stiffness.
3. The Continuous Role of Compression

Unlike ice, compression is used heavily after 72 hours, often for weeks or months. However, its purpose changes across the timeline:

  • Early on (0–72 hours): It provides high resistance to physically stop fluid from pooling in the empty spaces left by surgical dissection.
  • Later on (Post-72 hours): It acts as a supportive sleeve that maintains a baseline pressure, preventing fluid from backsliding into the area after MLD or active movement has successfully cleared it out.

Ultimately, medical protocols treat recovery like a construction site: ice and early compression act as floodgates to keep the initial wave manageable, while MLD acts as the drainage pump to clear the site once the storm has passed.

Note: According to 2026 revision of the American Physical Therapy Association (APTA) Clinical Practice Guideline (CPG) for total knee arthroplasty (TKA), published in Physical Therapy (PTJ), it lists updated recommendations post-op TKR. It notes there isn’t sufficient research supporting MLD (among other modalities like Kinesio taping). However, MLD is an adjunct to joint replacement speeding up the body’s natural response,1 & MLD may even be necessary. For example, in a patient who presents with a history of underlying venous stasis, or localized, hyper-inflammatory hard edema. To mitigate the physiological risk of localized lymphostasis, reflex vascular spasm, and subsequent subcutaneous fibrosis as detailed in established lymphology frameworks, manual lymphatic drainage is indicated to restore baseline transport capacity and permit functional progression of range of motion. As the Compendium of Dr. Vodder’s Manual Lymph Drainage states, “In inflammatory processes, protein-rich filtrate gets into precapillary tissue because of histaminic effects. The reflex spasm of the efferent lymph vessels prevents the increased filtrate from being caried off. This can lead to tissue fibrosis, which then impedes the filling of the initial lymph vessels. A further consequence is possible damage to the endothelial cells of the lymph angions. Therefore, after an inflammation has run its course, one often finds fibrous and obliterated lymph vessels in the subcutis cell tissue with diminished or nonexistent functionality. If tissue with a lymphostatic edema becomes inflamed, then lymph transport will become even more severely impaired.”9, 10 The problem is we need more research studies using (proper) MLD post-op to prove the efficacy of MLD.

References
1. Földi M, Földi E, Strössenreuther RHK, Kubik S, eds. Földi’s Textbook of Lymphology: For Physicians and Lymphedema Therapists. 3rd ed. Elsevier Urban & Fischer; 2012. (see pgs. 219-222 Physiological Responses to Impending Lymphostasis)
2. Guo S, Dipietro LA. Factors affecting wound healing. J Dent Res. 2010;89(3):219-229. doi:10.1177/0022034509359125
3. Kumar V, Abbas AK, Aster JC, eds. Robbins & Cotran Pathologic Basis of Disease. 10th ed. Elsevier; 2021:69-105.
4. Szolnoky G, Lakatos B, Keskeny T, et al. Effectiveness of manual lymphatic drainage in intensive phase I therapy of breast cancer–related lymphedema—a retrospective analysis. Breast Cancer. 2024;31(1):122-130. doi:10.1007/s12282-023-01512-y
5. Ebert JR, Joss B, Jardine B, Wood DJ. Randomized trial investigating the efficacy of manual lymphatic drainage to improve early outcomes after total knee arthroplasty. Arch Phys Med Rehabil. 2014;95(9):1743-1750. doi:10.1016/j.apmr.2014.04.024
6. Ultimate Health Clinic. Lymphatic drainage after surgery: what to expect. Ultimate Health Clinic Blog. Published October 21, 2026. Accessed October 26, 2026. ultimatehealthclinic.ca
7. Mechanics of mechanotherapy: post-surgical swelling management with physical therapy. MechanoTherapy Physio. Published March 20, 2026. Accessed October 26, 2026. mechanotherapy.physio
8. Bove AM, Carroll LA, Cone S, et al. Clinical practice guideline for physical therapist management of total knee arthroplasty: revision 2026. Phys Ther. 2026;106(7):pzag058. doi:10.1093/ptj/pzag058
9. Kasseroller R. Compendium of Dr. Vodder’s Manual Lymph Drainage. Karl F. Haug Verlag; 1989. (see page 89)
10. Kurz, I.: Lehrbuch der Manuellen Lymphdrainage nach Dr. Vodder, BD. 2 und 3 [Textbook of Dr. Vodder’s Manual Lymph Drainage, Vols. 2 and 3]. Karl F. Haug Verlag, Heidelberg 1989.

MLD after Plastic Surgery

Plastic surgery may be performed for many reasons. Reconstructive procedures can restore function or appearance after burns (September’s blog), trauma, cancer treatment, or congenital conditions. Cosmetic procedures may include tummy tucks, liposuction, breast augmentation, butt lifts, and removal of excess skin.

Sometimes plastic surgery is considered elective and not covered by insurance. Other times, it may be medically necessary. For example, skin-removal surgery after significant weight loss such as a panniculectomy (apron removal), abdominoplasty (tummy tuck), brachioplasty (arm lift) or a thigh lift can be either:

  • Elective/cosmetic: performed primarily to improve body contour or appearance.
  • Medically necessary/reconstructive: performed because excess skin causes documented problems such as recurrent rashes/intertrigo, infections, ulceration, difficulty with hygiene, impaired mobility, or other functional problems.

Regardless of the reason for surgery, the body responds to surgical trauma with inflammation and swelling. This is a normal part of healing—but excessive or prolonged swelling can be uncomfortable and may affect mobility and recovery. That’s where Manual Lymphatic Drainage (MLD) may have a role. MLD after plastic surgery can help manage postoperative swelling and support recovery.

MLD After Plastic Surgery: The Secret to Faster, Smoother Recovery

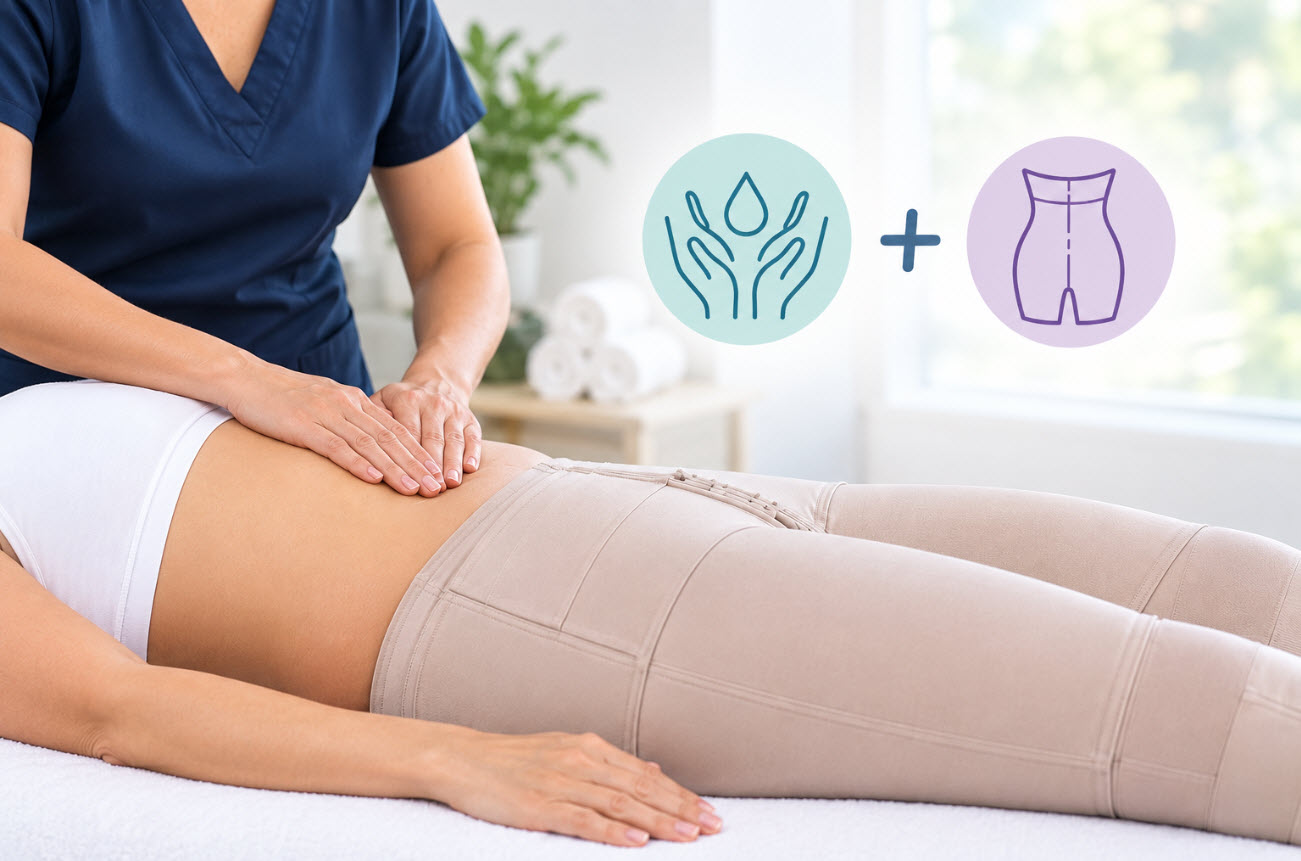
Manual Lymphatic Drainage is a specialized, incredibly gentle massage technique designed to stimulate the lymphatic system. Unlike a deep tissue massage, which works the muscles, MLD focuses entirely on the superficial layers of the skin where the initial lymph vessels reside. By using light, rhythmic strokes, a certified lymphedema therapist helps pump trapped fluid out of the surgical areas and back into the body’s natural filtration system.

(Note: It’s important it’s a certified lymphedema therapist with training in post-op plastic surgery because drainage pathways can change after certain procedures, scars impact the flow of fluid, etc.)

Why MLD is Beneficial Post-Plastic Surgery 1-4

  • Reduces Intense Swelling (edema): Surgical trauma disrupts your fluid balance. MLD moves stagnant fluid away from the incision sites, dramatically reducing post-op swelling and tight, uncomfortable pressure. It also helps drain inflammatory particles to speed up healing.
  • Minimizes Bruising: By clearing out trapped cellular debris and stagnant fluid, MLD helps your body process and fade deep bruising faster.
  • Reduces Fibrosis and Seroma Formation: Liposuction and body contouring can leave “dead space” under the skin where fluid loves to collect, creating hard lumps (fibrosis) or fluid pockets (seromas). MLD keeps fluid moving so tissues heal smoothly. (Note: If a seroma develops, it may need to be aspirated by your physician. This is important because they can become infected.)
  • Alleviates Pain and Relaxes: As swelling decreases, the painful pressure on your nerves is relieved. The gentle, repetitive motions of MLD also help soothe the nervous system, reflexively stimulating the parasympathetic system which calms the body. Electroencephalogram (EEG) studies show that manual lymph drainage (MLD) increases relaxing alpha brainwaves while decreasing fast beta and gamma waves linked to psychological stress.5-7
  • Speeds Up Scar Healing: Reduced swelling means fresh, nutrient-rich blood can reach your incisions, promoting cleaner, flatter, and less noticeable scars.

The Power Team: MLD and Compression

While MLD actively moves the fluid out, compression garments are essential to keep it from rushing back in. Following procedures like tummy tucks, lipo, or skin removal, your surgeon will likely fit you with a medical-grade compression garment. (Your certified lymphedema therapist may also be able to help.)

Compression acts as a supportive anchor. It holds the tissues in place, reduces dead space, and maintains the progress made during your MLD sessions. Together, MLD and compression form the ultimate post-op protocol to ensure your results look exactly as you and your surgeon intended.

When to Start

Every surgeon has specific post-op guidelines, but many recommend starting MLD within the first week following surgery—sometimes as early as days 2 to 4 for procedures like liposuction. Always clear any post-op therapies with your surgeon first. Your body worked hard to get you through surgery. Give it the gentle support it needs to heal beautifully, comfortably, and quickly! If you’d like a free pdf download of this blog, click here.

References
1. https://vodderschool.com/manual_lymph_drainage_effects
2. Textbook of Dr. Vodder’s Manual Lymph Drainage
3. Földi M, Földi E, Kubik S. Földi’s Textbook of Lymphology. Elsevier.
4. https://www.lymphedema-clinic.com/manual-lymph-drainage/effects.html
5. Abdominal MLD Study (showing alpha increase and beta/gamma reduction)
Kim M, Cho S. Effects of manual lymph drainage for abdomen on the brain activity of subjects with psychological stress. J Phys Ther Sci. 2017;29(3):491-494. doi:10.1589/jpts.29.491
6. Neck MLD Study (showing overall reduction in cortical excitation and increase in relaxation rhythms)
Kim M, Cho S. Effects of manual lymph drainage of the neck on EEG in subjects with psychological stress. J Phys Ther Sci. 2014;26(1):127-129. doi:10.1589/jpts.26.127
7. Frontal Asymmetry MLD Study (showing alpha band energy shifts to support positive emotional states) Kim M, Cho S. Manual lymph drainage attenuates frontal EEG asymmetry in subjects with psychological stress. J Phys Ther Sci. 2014;26(4):601-603. doi:10.1589/jpts.26.601

MLD After Burn Injury: Supporting Healing, Pain Relief, and Recovery

In Honor of the 25th Anniversary of 9/11 (those who suffered burn injuries on 09/11/2001)

A severe burn affects far more than the skin. Survivors may experience prolonged swelling, inflammation, pain, hypersensitivity, itching, restricted movement, and scarring. Recovery therefore requires more than wound closure—it requires restoring tissue health, mobility, comfort, and function.

Manual lymphatic drainage (MLD) is a gentle, specialized technique designed to support lymphatic fluid transport. When appropriately incorporated into burn rehabilitation, MLD may help address several of the factors that can interfere with recovery.

Reducing edema and tissue congestion

After a significant burn, inflammation can cause substantial accumulation of fluid and proteins in the tissues. Excessive edema can increase tissue pressure, restrict movement, and contribute to discomfort. MLD is designed to facilitate lymphatic transport and the movement of excess interstitial fluid.1

Burn-rehabilitation research supports edema management as an important component of recovery, with interventions such as compression associated with improvements in edema, range of motion, and hand function.2

Supporting the inflammatory environment

The lymphatic system transports excess interstitial fluid, proteins, cellular debris, and substances associated with inflammation. MLD facilitates clearance from congested tissues by increasing lymphatic transport and inflammatory signaling. This creates a more favorable environment for recovery.

Reducing pain

MLD influences pain through several mechanisms: Reducing edema can decrease tissue pressure. The gentle, rhythmic techniques used in MLD has a calming effect on the sympathetic nervous system and  promotes parasympathetic activity associated with relaxation and pain modulation.6 Research examining pain and autonomic function has found an association between greater parasympathetic activity and greater capacity for pain inhibition as well.3, 7

More specifically, nociceptors (pain receptors) send signals to the brain for the duration of a pain stimulus. Nerve fibers have a collateral pathway to an inhibitory cell which is connected to the  “switch-cell” of the pain pathway.  When MLD is performed correctly, touch receptors transform this impulse into an inhibition & interrupt the transmission of pain. Note:  The inhibitory effect of MLD is not likely to work on very strong pain.6

Supporting movement and rehabilitation

Pain and swelling can create a cycle of guarding, stiffness, and reduced movement. By helping manage edema and discomfort, MLD can make movement easier and allow patients to participate more fully in therapeutic exercise and functional rehabilitation. This is particularly important after hand and extremity burns, where swelling and scar formation can significantly limit function.8

Supporting scar management

Persistent inflammation and edema can contribute to an unfavorable tissue environment during healing. MLD can complement other scar-management strategies by addressing edema and tissue congestion. Research on massage-based scar treatment in burn survivors has demonstrated improvements in symptoms such as pain and itching and helping to prevent development of certain scar characteristics (e.g. hypertrophic scars). A burn-trauma service evaluation involving myofascial-manual lymphatic drainage reported potential benefits involving secondary inflammation, scar hypertrophy, and tissue regeneration.9

The Bigger Picture

The potential benefits of MLD shouldn’t be ignored: reduced edema, less tissue congestion, improved comfort, support for mobility, relaxation, and possible influence on pain and autonomic regulation. However, MLD should not be considered a replacement for specialized burn care. It is best viewed as an adjunct to comprehensive rehabilitation, which may include: wound care, pain management, compression, elevation and positioning, therapeutic exercise, range-of-motion, scar management, physical and occupational therapy, and psychological support.

References

  1. Földi M, Földi E, Kubik S. Földi’s Textbook of Lymphology. Elsevier. (shop.elsevier.com)
  2. Edger-Lacoursière Z, Deziel E, Nedelec B. Rehabilitation interventions after hand burn injury in adults: A systematic review. Burns. 2023. https://pubmed.ncbi.nlm.nih.gov/35662480/
  3. Forte G, et al. Heart Rate Variability and Pain: A Systematic Review. Brain Sciences. 2022. https://pubmed.ncbi.nlm.nih.gov/35203917/
  4. Myofascial-manual lymphatic drainage for burn trauma: a service evaluation. (pubmed.ncbi.nlm.nih.gov)
  5. Massage, laser and shockwave therapy improve pain and scar pruritus after burns: a systematic review. Journal of Physiotherapy. 2024. (pubmed.ncbi.nlm.nih.gov)
  6. Textbook of Dr. Vodder’s Manual Lymph Drainage
  7. Mühlenpfordt I, Blakeslee SB, Everding J, Cramer H, Seifert G, Stritter W. Touching body, soul, and spirit? Understanding external applications from integrative medicine: A mixed methods systematic review. Front Med (Lausanne). 2022;9:960960. Published 2022 Dec 22. doi:10.3389/fmed.2022.960960. https://pmc.ncbi.nlm.nih.gov/articles/PMC9813495/
  8. Edger-Lacoursière Z, Deziel E, Nedelec B. Rehabilitation interventions after hand burn injury in adults: A systematic review. Burns. 2023;49(3):516-553. doi:10.1016/j.burns.2022.05.005. https://pubmed.ncbi.nlm.nih.gov/35662480/
  9. Loskotová A, Loskotová J, Suchanek I, Brychta P, Lipový B. Myofascial-manual lymphatic drainage for burn trauma: a service evaluation. Br J Community Nurs. 2017;22 Suppl 5(Sup5):S6-S12. doi:10.12968/bjcn.2017.22.Sup5.S6. https://pubmed.ncbi.nlm.nih.gov/28467220/

Rethinking MLD Pressure (part 2)

Last month, we started a discussion about MLD pressure. Foldi always taught light pressure. Newer research indicates lymph vessels aren’t occluded until 86 mmHg. We’re continuing that topic this month.

Why This Does Not Mean “Deeper Pressure Is Better”

One of the most important conclusions from the study is often overlooked:

The researchers specifically noted that manual lymph drainage pressures applied by the hand are typically under 10 mm Hg, which remains well below lymphatic occlusion thresholds. (Sage Journals)

That matters because MLD is not intended to “force fluid through pipes.” Instead, it works by:

  • stimulating lymphatic vessel activity,
  • improving lymphangion filling,
  • enhancing rerouting through collateral pathways,
  • and supporting natural lymphatic pumping.

The study supports the idea that properly performed gentle MLD does not collapse lymphatics. In other words, Foldi’s gentle-pressure philosophy remains physiologically sound.

The Difference Between Compression and MLD

The study also helps clarify confusion between:

  • manual lymph drainage pressure, and
  • compression therapy pressure.

Compression garments and pneumatic compression devices may use substantially higher pressures than hands-on MLD. The researchers warned that if compression pressures exceed lymphatic occlusion pressure, collectors and initial lymphatics could temporarily collapse during inflation phases. (Sage Journals)

This distinction is critical in clinical practice.

Foldi-based Complete Decongestive Therapy (CDT) has always emphasized that:

  1. MLD prepares and stimulates lymphatic pathways,
  2. compression maintains fluid reduction,
  3. exercise activates the muscle and lymphatic pumps,
  4. and skin care protects vulnerable tissues.

The therapies work together — but they do not work the same way.

What This Means for Therapists Today

The 2016 findings encourage a more evidence-based discussion around lymphatic pressure without abandoning traditional lymphology principles.

For certified lymphedema therapists, the takeaway is not to use heavier pressure. Instead, the study reinforces several clinical ideas:

1. Gentle Pressure Can Still Be Effective – MLD does not require deep force to stimulate lymphatic transport.

2. Vessel Filling Matters – Lymphatic flow is intermittent. Proper sequencing and preparation techniques — central clearing, proximal-to-distal preparation, and rhythmic repetition — may improve lymphatic filling and flow.

3. Precision Matters More Than Intensity – Direction, sequencing, stretch, and rhythm likely influence outcomes more than raw pressure.

4. Compression Must Be Individualized – Higher pressure is not automatically better, especially in compromised or fibrotic tissues.

Modern Imaging Is Validating Traditional Lymphology

One of the most fascinating aspects of this research is how modern imaging technology is beginning to visually confirm concepts long taught in Foldi-based education.

The lymphatic system is dynamic, contractile, and responsive — not passive.

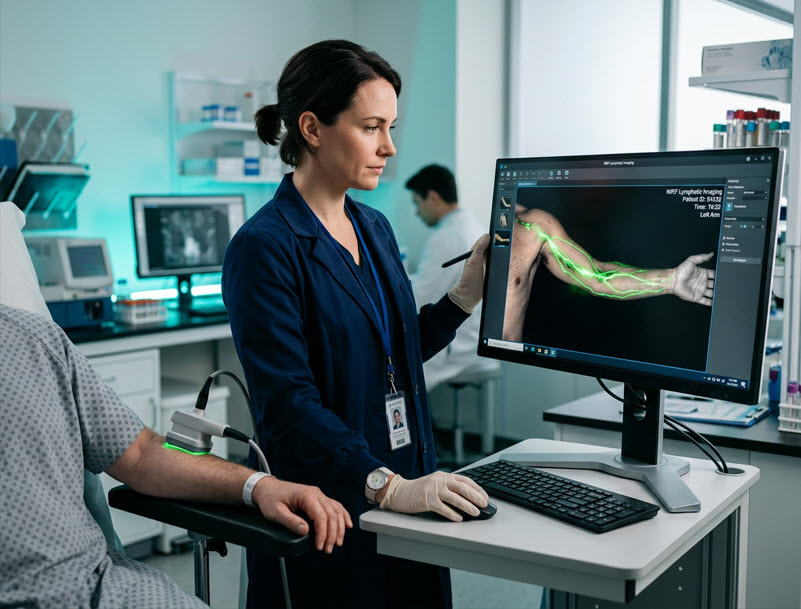
Near-infrared fluorescence imaging allows researchers to watch lymphangions contract and observe fluid movement in real time, offering a new scientific window into therapies that were previously understood mostly through clinical outcomes and practitioner experience. (Sage Journals)

As lymphatic science evolves, the future of lymphedema care will likely combine:

  • traditional clinical wisdom,
  • advanced imaging,
  • individualized pressure strategies,
  • and deeper understanding of lymphatic biomechanics.

The Foldi principles are not being replaced. They are being explained more clearly than ever before.

References
1 Foldi, M, Foldi, E. (2006). Foldi’s Textbook of Lymphology (2nd ed.), p. 526. Germany: Urban and Fisher.
2 Belgrado, J.-P., Vandermeeren, L., Vankerckhove, S., Valsamis, J.-B., Malloizel-Delaunay, J., Moraine, J.-J., & Liebens, F. (2016). Near-infrared fluorescence lymphatic imaging to reconsider occlusion pressure of superficial lymphatic collectors in upper extremities of healthy volunteers. Lymphatic Research and Biology, 14(2), 70–77. https://doi.org/10.1089/lrb.2015.0040

Rethinking MLD Pressure (part 1)

What Foldi’s Principles and New Lymphatic Research Tell Us

For decades, manual lymph drainage (MLD) has been guided by one central principle from the Foldi school of lymphedema treatment: lymphatic vessels are delicate, superficial, and highly responsive to pressure.1 Therapists are taught to use slow, rhythmic, skin-stretching movements rather than deep tissue force. Now, modern imaging research is helping explain why that approach works — and where MLD pressure thresholds may actually lie.

A landmark 2016 study published in Lymphatic Research and Biology used near-infrared fluorescence lymphatic imaging (NIRFLI) to directly observe lymphatic flow in real time.2 The researchers discovered that superficial lymphatic collectors tolerated much higher occlusion pressures than previously believed, with an average occlusion pressure of approximately 86 mm Hg in healthy subjects. (Sage Journals). At first glance, that finding may seem to contradict traditional Foldi-based MLD concepts emphasizing gentleness in applying MLD pressure. In reality, the research actually reinforces many of Foldi’s core principles.

The Foldi Philosophy: Pressure Is Not the Goal

The Foldi method, developed by Michael Földi and Ethel Földi, teaches that successful lymphatic treatment depends on:

  • stimulating superficial lymphatic vessels,
  • encouraging lymphangion contraction,
  • reducing tissue congestion,
  • and redirecting fluid toward healthy drainage territories.

The emphasis has always been on precision over force.

Traditional Foldi training warns against aggressive massage because excessive pressure may:

  • collapse superficial lymphatics,
  • increase capillary filtration,
  • irritate tissues,
  • or worsen inflammation and fibrosis.

The 2016 NIRFLI study adds important nuance to this understanding.

What the 2016 Study Actually Found

Researchers observed lymph flow in healthy volunteers using fluorescent imaging while gradually increasing pressure with a transparent cuff. They combined this with a specialized MLD approach called the “Fill & Flush Drainage Method” to keep lymphatic vessels actively filled during testing. (Sage Journals)

Their findings included:

  • Mean lymphatic occlusion pressure: 86 mm Hg
  • No significant differences between age, gender, or side of the body
  • Previous studies may have underestimated occlusion pressure due to imaging limitations and insufficient vessel filling during testing (Sage Journals)

Earlier estimates had suggested lymphatic occlusion occurred around 24–40 mm Hg. This new research challenged that assumption. (Sage Journals)

This doesn’t mean deeper or more pressure is better. Find out why in the next blog…

References
1 Foldi, M, Foldi, E. (2006). Foldi’s Textbook of Lymphology (2nd ed.), p. 526. Germany: Urban and Fisher.
2 Belgrado, J.-P., Vandermeeren, L., Vankerckhove, S., Valsamis, J.-B., Malloizel-Delaunay, J., Moraine, J.-J., & Liebens, F. (2016). Near-infrared fluorescence lymphatic imaging to reconsider occlusion pressure of superficial lymphatic collectors in upper extremities of healthy volunteers. Lymphatic Research and Biology, 14(2), 70–77. https://doi.org/10.1089/lrb.2015.0040

MLD and a Woman’s Menstrual Cycle (part 2)

Last month, we looked at what happens during a woman’s period. This month, we’ll talk about how MLD can help.

Symptoms MLD May Help

In the second half of a cycle (the luteal phase), all kinds of unwelcomed symptoms can emerge. These can include bloating, cramps, weight gain, mood swings, fatigue, constipation, headaches & food cravings. These symptoms are caused by the rise & sudden, sharp drop of progesterone (& estrogen) when there is no egg fertilization (i.e. pregnancy). This hormone shift can affect brain chemistry, especially serotonin, which influences mood and emotion.

  • Bloating & Water Retention – Progesterone affects fluid balance by acting on the kidneys and blood vessels. Its drop can cause fluid to accumulate, leading to bloating, breast tenderness, and mild weight gain.
  • Cramps (Dysmenorrhea) – As hormone levels fall, the body produces prostaglandins to help shed the uterine lining. These chemicals cause the uterus to contract, which can lead to pain and cramping. Higher prostaglandin levels = more intense cramps.
  • Constipation – High progesterone (& estrogen) slows down smooth muscle contractions in the digestive tract (motility). This can lead to slower digestion and constipation, especially in the days following ovulation.
  • Headaches – Estrogen influences how blood vessels expand and contract and affects neurotransmitters like serotonin. When estrogen drops, it can trigger headaches or migraines, especially in those sensitive to hormonal changes.
  • Fatigue – The body goes through energy-intensive changes during the luteal phase, and the falling hormones can also impact thyroid function and serotonin, leading to tiredness or sleep disruption.
  • Food Cravings – Estrogen and progesterone influence insulin sensitivity and appetite-regulating neurotransmitters like dopamine and serotonin. The drop can cause cravings (especially for sugar and carbs), which temporarily boost serotonin and make you feel better — at least short-term.
  • Mood Swings & Irritability – Estrogen and progesterone affect brain chemistry, including: Serotonin (mood), GABA (calmness and anxiety) & Dopamine (pleasure and motivation). When these hormones drop, serotonin levels can dip, contributing to irritability, anxiety, sadness, or mood swings. Sensitivity to this drop varies. Some women experience mild PMS while others experience more severe PMS.

How MLD May Help

MLD increases lymphangiomotion (lymph pumping). By doing so, inflammatory particles & excess fluid are removed. In addition, proper MLD has a very relaxing effect on the body. So, it could help mood. Unfortunately, I’m not aware of any impact on food cravings!

  1. Bloating and Water Retention – MLD gently stimulates the lymphatic system, which is responsible for removing excess fluid and waste from tissues. By improving lymph flow, it can reduce puffiness, bloating, and that heavy, swollen feeling often reported in the days before menstruation.
  2. Breast Tenderness – Swollen, tender breasts are often caused by fluid buildup and hormonal shifts. MLD around the neck, armpits, and chest area can reduce this fluid accumulation and ease discomfort.
  3. Headaches (from fluid pressure) – If headaches are partially due to congestion in the head and neck, MLD may help by encouraging drainage and reducing pressure.
  4. Fatigue (mild benefit) – Some women report feeling more energized after MLD, likely due to improved circulation and detoxification, though this effect varies from person to person.
  5. Constipation – After ovulation, progesterone levels rise before dropping. During this rise, progesterone has a relaxing effect on smooth muscle, including the muscles of the gastrointestinal (GI) tract. This causes slower gut motility (i.e. food moves more slowly through the intestines) which can lead to harder stools, less frequent bowel movements and bloating and gas. Gentle abdominal MLD techniques may improve circulation of lymphatic fluid around the intestines and abdominal organs, reducing congestion, inflammation, or sluggish movement. It can also help reduce fluid retention and bloating in the abdomen, which can make constipation feel worse. With less abdominal pressure, the bowel may move more freely.3
  6. Mood – While MLD may not directly affect mood, it can help with reducing stress and tension, which may indirectly support better mood regulation & feelings of well-being.

Caution

MLD is not a standalone treatment for PMS. It works best when combined with hydration, fiber, movement, and sometimes probiotics or dietary adjustments. Pending a doctor’s approval, NSAIDS like Ibuprofen or heating pads may be helpful for severe cramps. And, in some cases, birth control pills can help regulate a cycle & improve symptoms. With any medication, it’s important to be aware of side effects. And be aware that deep abdominal techniques are contraindicated during menses.

Cycle Idiopathic Edema

While talking about PMS, it’s a good idea to mention another condition: Idiopathic cyclic edema (ICE). ICE is a condition that resembles PMS but is different. Besides similar symptoms, women often have two good weeks followed by two bad weeks of swelling. Oddly, even though considered edema, it is a protein-rich fluid. So, MLD & compression can be helpful.1 It mostly affects women & causes daily, unpredictable swelling, especially in the legs, hands, face, and sometimes abdomen, with no identifiable underlying disease. (The term “idiopathic” means the exact cause is unknown, and “cyclic” refers to the pattern of swelling that comes and goes, often worsening throughout the day.) Although the cause is not clear, a number of hormones (particularly the luteinizing hormone)1 are postulated to be involved. Altered vascular permeability and increased lymph formation may also be part of the disorder.2

References
1 Kasseroller, R. (1998). Compendium of Dr. Vodder’s Manual Lymph Drainage, pg.111. Germany: Huthig GmbH.
2 Sabatini S. Hormonal insights into the pathogenesis of cyclic idiopathic edema. Semin Nephrol. 2001;21(3):244-250. doi:10.1053/snep.2001.21651
3 Wittlinger, H., Wittlinger, G. (1998). Textbook of Dr. Vodder’s Manual Lymph Drainage (6th ed.), pg. 87. Germany: Karl Haug Verlag.

MLD and a Woman’s Menstrual Cycle (part 1)

(Caution: This month’s blog may be a bit awkward for male readers.) A patient recently came into the office seeking relief from symptoms related to her menstrual cycle. Her primary complaints were bloating and weight gain. She had a wedding coming up and wanted to look her best. Can manual lymph drainage (MLD) help with symptoms related to a woman’s period? Let first look at what occurs during a woman’s cycle.

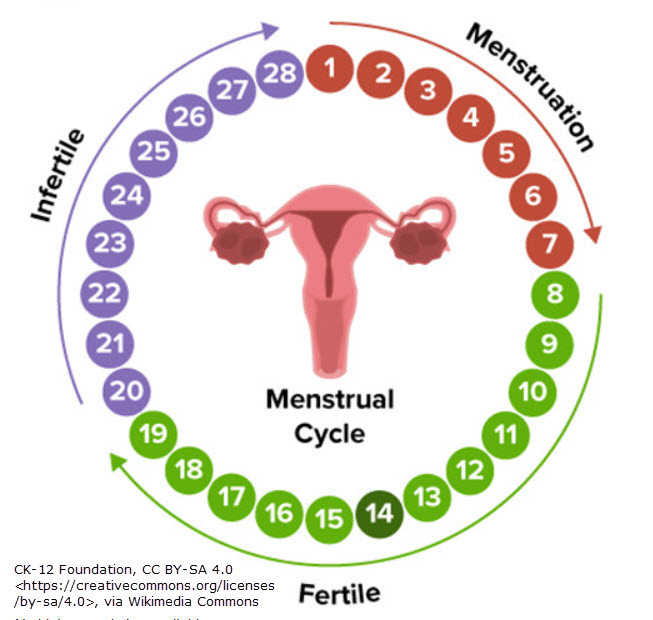
The Cycle

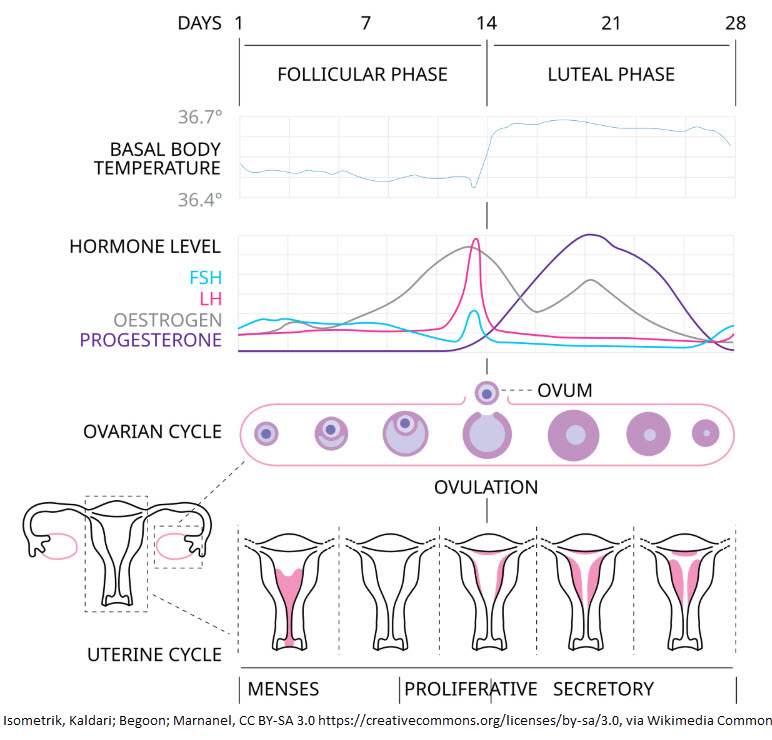
Every month (if things work like they should), a woman goes through a series of steps through which the body prepares for possible pregnancy. The cycle typically lasts 28 days (but the range varies from 21 to 35 days). And it’s regulated by hormones. (If you’ve read past blogs, you may have learned hormones can cause swelling because of how they influence the permeability of the capillary bed, allowing fluid and proteins to escape the blood stream and enter the tissue space.)

Days 1-5: The period. This is when there is active bleeding as the uterine lining sheds. Hormone levels are lower, especially estrogen.

Symptoms: Cramping, bloating, fatigue, mood changes which subside towards the end.

Days 1-13: Follicular Phase. The pituitary gland releases FSH (follicle-stimulating hormone), stimulating the ovaries to produce follicles. One becomes dominant and matures into an egg. Estrogen increases, helping rebuild the uterine lining. Days 8-14 are the best times to get pregnant as there’s an increased chance the sperm will be present when an egg is released (on day 14), but days 8-19 are a conservative window.

Symptoms: Higher energy, mental clarity, clearer/glowing skin, increased sex drive, higher confidence, cervical mucus becomes clearer, stretchier, and more slippery (like egg whites) to help sperm travel easier as ovulation approaches.

Day 14: Ovulation. A few days before ovulation, there’s a surge in LH (luteinizing hormone) triggering the release of the mature egg from the ovary (ovulation) on day 14. This is the most fertile time; sperm can survive up to 5 days, and the egg lives about 24 hours.

Symptoms: Same as the follicular phase. In addition, the breasts and labia may become more sensitive, tender and/or enlarged.

Day 15-28: Luteal Phase.  If there is no pregnancy, the empty follicle becomes the corpus luteum (Latin for “yellow body”), which secretes progesterone to thicken the uterine lining for possible pregnancy. If that doesn’t happen, the corpus luteum breaks down, progesterone drops and menstruation begins.

Symptoms: If no pregnancy occurs, PMS symptoms occur (the symptoms women usually want relief from).

PMS Symptoms

PMS stands for Premenstrual Syndrome. But there are numerous acronyms that substitute meaning: “Pass My Snacks,” “Prepare to Meet Satan,” “Pardon My Sensitivity,” “Pizza and Mood Swings,” and “Please Make it Stop” are among the contenders. The symptoms of PMS can include bloating, cramps, weight gain, mood swings, fatigue, constipation, headaches, food cravings. They’re caused by the rise and sudden, sharp drop of progesterone when there is no pregnancy. This hormone shift can affect brain chemistry, especially serotonin, which influences mood and emotion. When the changes are extreme or severe, it’s called Premenstrual Dysphoric Disorder.

How can MLD help? Find out next month!

Quick Links

  • Careers
  • Blog
  • Terms of Use
  • Disclaimer
  • Privacy

Contact Us

309 W. Eldorado Pkwy
Little Elm, Texas 75068-5196
214-422-8265
214-614-9352 fax
info@LTStherapy.com

cropped-Cropped-beach-lts-header.png

Copyright © 2026 · Lymphedema Therapy Source